
What is daratumumab?
Daratumumab is a monoclonal antibody that targets abnormal plasma cells, including myeloma cells and those involved in AL amyloidosis.
Plasma cells are immune cells that make antibodies to help protect the body from infections. In myeloma and AL amyloidosis, some of these cells become abnormal and produce faulty proteins that can build up and harm the body.
Antibodies are proteins that the body creates to recognise and fight foreign substances (e.g. viruses and bacteria). Monoclonal antibodies are lab-made antibodies engineered to mimic human antibodies. They bind to specific targets on abnormal cells to recruit the body’s immune system to kill them. Immune cells do this by secreting special molecules that can kill these abnormal cells.
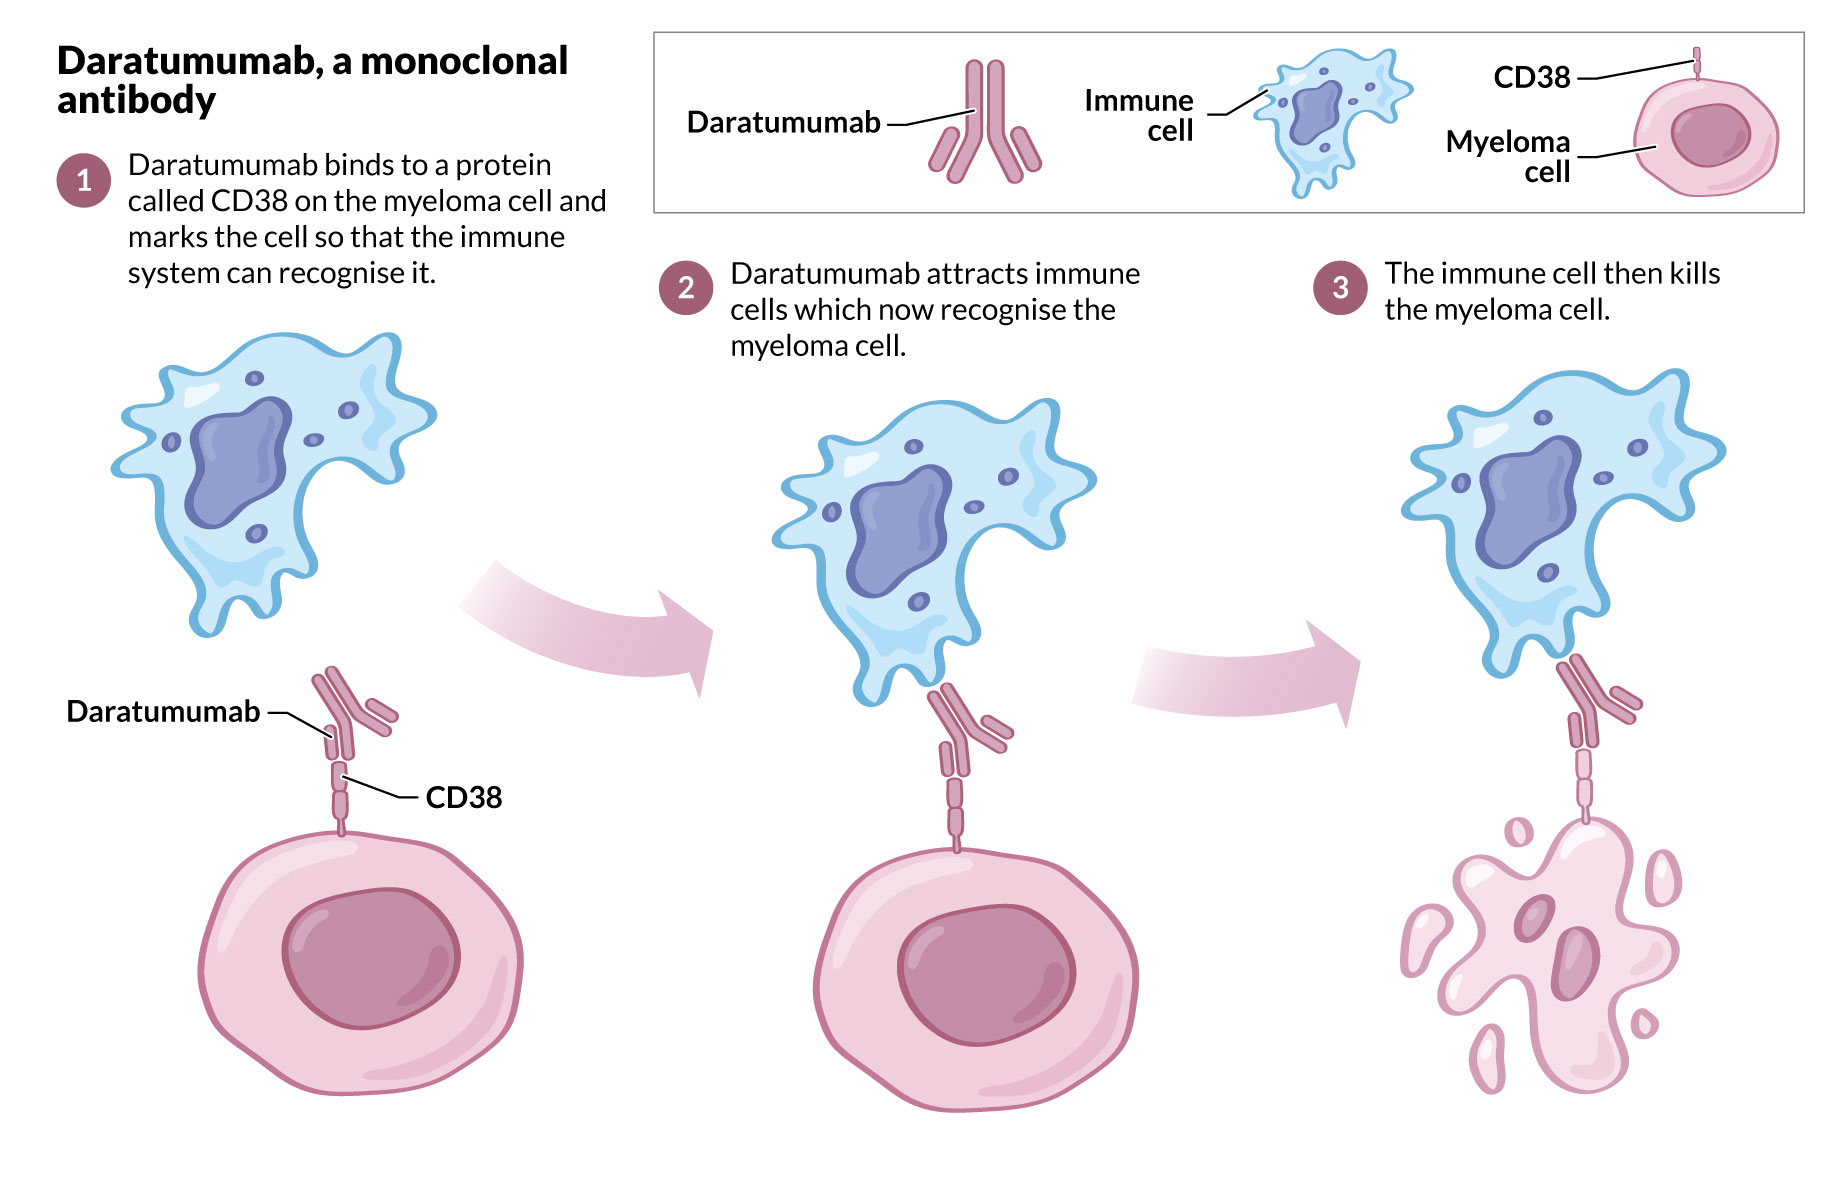
Daratumumab binds to a protein called CD38, which is present on the surface of abnormal plasma cells. Once daratumumab binds to these cells through CD38, it can kill them directly, as well as activate immune cells to help destroy them.
How is daratumumab used?
Daratumumab is used in treatment pathways. Below, we highlight the indications that are approved in the European Union.
In myeloma, Daratumumab is used in many different settings across the myeloma treatment pathway, usually in combination with other myeloma medicines but sometimes on its own. In newly diagnosed myeloma patients, it is usually given as either:
- Daratumumab with lenalidomide and dexamethasone (referred to as Dara-Rd) in patients who are not eligible for autologous stem cell transplantation (ASCT)
- Daratumumab with bortezomib, melphalan and prednisone (referred to as Dara-VMp) in patients who are not eligible for autologous stem cell transplantation (ASCT)
- Daratumumab with bortezomib, lenalidomide and dexamethasone (referred to as Dara-VRd) for both transplant eligible and ineligible patients.
- Daratumumab with bortezomib, thalidomide and dexamethasone (referred to as Dara-VTd) for transplant eligible patients.
It is used in myeloma patients who did not respond to previous myeloma therapy or whose myeloma worsened (relapsed and/or refractory):
- Daratumumab with lenalidomide and dexamethasone (referred to as Dara-Rd)
- Daratumumab with bortezomib and dexamethasone (referred to as Dara-Vd) in patients who have received at least one prior line of therapy.
- Daratumumab with pomalidomide and dexamethasone (referred to as Dara-Pd) in patients who did not respond to lenalidomide combined with a proteasome inhibitor (such as bortezomib) or in patients where the myeloma worsened after at least two prior lines of therapy.
- Daratumumab as a standalone treatment (monotherapy) when the myeloma relapsed after treatment with proteasome inhibitors and immunomodulatory medicines (e.g. lenalidomide or pomalidomide).
In smouldering myeloma, daratumumab is used as monotherapy if patients are at high risk of progressing to myeloma.
in AL amyloidosis, daratumumab is used in newly diagnosed patients in combination with cyclophosphamide, bortezomib and dexamethasone (referred to as Dara-CyBorD).
How is daratumumab given?
Daratumumab is mainly given as a fixed dose and as a subcutaneous (SC) injection (i.e. under the skin) in the stomach area which takes 3 to 5 minutes. SC administration may also be given at home by nurses and self-administration is increasingly being explored by hospitals. This may reduce travel time and make treatment more convenient for patients.
It can also be given as an infusion (drip) into a vein. This is known as intravenous (IV) administration. The medicine is given at a hospital outpatient department or clinic and it can take over an hour. The IV dose of daratumumab will depend on your weight
How often and for how long is daratumumab given?
How often you receive daratumumab depends on the following:
- The treatment combination you receive
- Your indication (i.e. newly diagnosed or relapsed/refractory myeloma, smouldering myeloma or AL amyloidosis)
- whether you can have a stem cell transplant or not
Daratumumab is usually given once a week for six to eight weeks, then every two or three weeks, depending on the indication and treatment combinations, and then monthly until the disease progresses.
Your doctor will give you more information on the treatment schedule tailored to your disease and may recommend less frequent treatment if you experience certain side effects.
Treatment with daratumumab may be stopped in patients who have maintained minimal residual disease (MRD) negativity for 12 months and have received maintenance therapy for at least two years
MRD is the term given to describe the small number of cancer cells that may remain in a patient’s body during or after treatment even when no cancer is detectable with standard tests. MRD negativity means no cancer cell was detected in 100,000 or 1 million cells.
What are the benefits of daratumumab?
Myeloma
Several clinical trials have explored the benefits of daratumumab monotherapy and daratumumab in combination with other myeloma medicines.
Clinical trials consistently find that adding daratumumab to standard treatments for myeloma leads to better outcomes for patients.
In patients with newly diagnosed or relapsed/refractory myeloma, those who received daratumumab generally lived longer and had their disease under control for longer. Daratumumab helped in delaying the progression of myeloma and made the treatment more effective by reducing or even clearing myeloma cells in the body. These benefits were seen in patients with and without autologous stem cell transplant.
Smouldering myeloma
Several clinical studies explored how safe and effective daratumumab is in patients with smouldering myeloma who were at high risk of developing myeloma. These studies collectively report that using daratumumab to treat high risk smouldering myeloma patients can significantly delay their risk of developing myeloma.
AL amyloidosis
A clinical trial assessed how safe and effective daratumumab is in combination with cyclophosphamide, bortezomib and dexamethasone (Dara-CyBorD) for the treatment of newly diagnosed AL amyloidosis patients. This clinical trial compared Dara-CyBorD to CyBorD, which was the standard treatment given to newly diagnosed AL amyloidosis patients at that time. The results of the trial demonstrated the benefit of adding daratumumab to the CyBorD combination.
Patients who received the combination with daratumumab lived longer overall and had improved heart and kidney function compared to patients who received CyBorD without daratumumab.
What side-effects may occur?
Generally, daratumumab is well tolerated and severe side-effects are rare. Here we describe the most common side-effects of daratumumab.
These happen in more than one in ten patients receiving daratumumab, unless specified otherwise.
Side effects vary from person to person and are often manageable with support from your healthcare team. If you notice any new or worsening symptoms, or anything that might be a side effect of daratumumab, tell your doctor or healthcare team immediately. They can help you manage it.
Infusion-related reactions
Some patients may have an allergic-like reaction when they receive daratumumab as an intravenous (IV) infusion or subcutaneously (SC).
Infusion-related reactions occur less frequently when daratumumab is given SC.
A rash or redness might appear at the injection site. These usually develop within minutes or hours but may develop up to a day (24 hours) after treatment. They are rarely severe. You will receive medications beforehand to help prevent them and the medical team will monitor you closely.
You should be monitored for six hours after receiving your first dose. Even if you have a reaction after the first dose, it is unlikely to occur again with the next doses.
Symptoms include cough, chills, difficulty breathing, runny or blocked nose, sore throat, nausea (feeling sick) and vomiting.
You should contact your doctor or healthcare team immediately if you think you may be having a reaction.
Infections
As a result of treatment with daratumumab, you are at a higher risk of developing certain infections which can
give you a high temperature (i.e. fever) and make you feel unwell. While daratumumab targets myeloma cells, it can also kill normal immune cells and lower antibody levels that help fight germs. This makes it harder for your body to fight infections.
Specific infections might include:
- COVID-19. Vaccination against SARS-CoV-2 can help prevent COVID-19.
- Infections of the nose, throat and sinuses (upper respiratory infections)
- Pneumonia (infection of the lung). Common signs of pneumonia include high or low temperature, coughing (which may include coughing up yellow or green mucus) and wheezing, shortness of breath, fatigue, loss of appetite and confusion. To prevent or treat infections, your doctor might prescribe antibiotics (medicines that treat bacterial infections). In severe cases, you may also need to stay in hospital and be given oxygen to help you breathe. Vaccinations against streptococcus pneumoniae (a type of bacteria that causespneumonia) and respiratory syncytial virus (RSV) can help prevent pneumonia.
- Bronchitis (inflammation of the airways in the lungs). It occurs when the lining of your bronchial tubes becomes inflamed. These tubes are part of your airways and carry air into and out of your lungs. Usually, bronchitis is caused by viruses that cause colds and flu. Symptoms include coughing, a sore throat, fatigue, chest discomfort, shortness of breath and wheezing. Annual flu vaccinations can help prevent bronchitis as many cases arise from flu infections.
Because daratumumab can affect the immune system, viruses already in your body, including the one that causes shingles, may become active, even if you have been vaccinated. Your doctor may recommend antiviral medication to help prevent this.
While you are taking daratumumab you should take precautions to help avoid infections. This might include washing your hands more often, avoiding large, crowded places and avoiding contact with people who have viral infections. Getting vaccinated can help prevent infections. See our resources on infection prevention. When taking daratumumab, it is important to seek medical assistance immediately if you develop cold or flu-like symptoms, start to feel unwell and/or have a high or low temperature, as this is usually caused by your body’s response to an infection.
Blood changes that increase your risk of infection
You are at more risk of infection while receiving isatuximab because of changes in your blood and immune system that might make it more difficult for you to fight off infections.
Low levels of white blood cells (leukopenia)
Neutropenia and lymphopenia mean a low level of different types of white blood cells (called neutrophils and lymphocytes), which are important for the immune system and fighting infections. If your white blood cell count is low, you are more likely to catch an infection and become unwell. It might also take longer for you to get better after an infection. Your doctor will take your blood before and during treatment to monitor your white blood cell levels.
In severe cases, neutropenia can be treated with G-CSF (Granulocyte Colony-Stimulating Factor). G-CSF is a medicine that stimulates cell growth and can help the bone marrow make more neutrophils to help fight infections. It is injected under the skin (subcutaneously).
Other blood changes
Low platelets (increased risk of bleeding)
Thrombocytopenia means you have a low platelet count. Platelets (also known as thrombocytes) play an important role in slowing or stopping bleeding (i.e. blood clotting)
and healing wounds. A low number of platelets can increase your risk of bleeding. Your doctor will check your blood (including platelet levels) before and during treatment. If you experience abnormal bruising or bleeding
(e.g. from your gums, nose or after tests), you should inform your doctor. If severe, this may be managed through treatment dose delays. It might also be possible to use platelet transfusions, which is given by an infusion.
Your doctor may recommend following some guidance to avoid injury and bleeding.
Low level of red blood cells (anaemia)
Anaemia means that you have a low level of red blood cells or low level of haemoglobin. Red blood cells play an important role in carrying oxygen around your body. If you have a low level of red blood cells you might lack energy and feel weak, fatigued, breathless or light-headed. You may also have noticeably paler skin than normal.
Your doctor will take your blood before and during treatment to monitor your red blood cell levels. However, if you experience these symptoms at any point you should speak to your doctor. Treatment for anaemia may include iron tablets, blood transfusions (which gives you extra red blood cells) or a drug called erythropoietin (EPO). EPO can help your body make extra red blood cells. It is given via an injection under your skin (subcutaneously).
Fatigue
Fatigue is a feeling of extreme and persistent tiredness, which may not be relieved by rest. As with all side effects, you should tell your doctor or nurse if you are feeling very tired. Treating other side effects can help with this.
For example, your fatigue may be caused by a low number
of red blood cells (anaemia – see above). If this is treated, you might start
to feel less tired. Your doctor might also be able to reduce the dose of certain drugs if they are a contributing factor.
Small amounts of easy exercise and periods of rest can also help. Planning and anticipating your daily activities can help manage your fatigue, scheduling rest periods during the day – particularly after more strenuous activities.
Muscle-related side effects
You may experience muscle cramps or spasms as a reaction to daratumumab. A muscle cramp or spasm is
a sudden contraction of one or more muscles, which can cause intense pain. Most muscle cramps are not serious and self-care steps such as stretching or drinking enough fluids can help relieve symptoms.
Gastrointestinal disorders
Diarrhoea
Diarrhoea is where someone has three or more loose stools (i.e. bowel movements) every day. Having a balanced diet can help with this symptom, as can avoiding foods that upset your stomach like fatty and spicy food and avoiding fruit juice. If you have diarrhoea, make sure you drink plenty of water each day – around 2 to 3 litres each day. Your doctor may also prescribe you medicines to help control your diarrhoea, called anti-diarrhoeals.
Nausea
Nausea is when someone has an unpleasant urge to vomit. If you vomit, it is very important to stay hydrated by drinking water (with dissolved electrolytes). Try to take small sips if you feel unable to drink normally.
Anti-emetics are anti-sickness drugs, which you may be prescribed to prevent or stop your nausea and sickness.
Constipation
Constipation is a bowel dysfunction that makes bowel movements infrequent or difficult to pass. Stools are often hard. Symptoms can include abdominal pain. Your doctor may prescribe you constipation treatment or recommend dietary changes. Staying hydrated is important.
Neuropathy
Neuropathy is when a nerve or several nerves are damaged, leading to pain, weakness, numbness or tingling in one or more parts of your body. It can be managed by delaying treatment administration, using pain relievers or neuroprotective supplements which protect the brain and nervous system from damage.
Other very common side-effects (which may affect more than 1 in 10 patients) are insomnia (sleeplessness), joint pain, back pain and cough
Uncommon side-effects
These side effects may affect more than 1 in 100 patients. Among uncommon side effects rare cases of hepatitis (inflammation of the liver) have been reported. This is because daratumumab can reactivate hepatitis B virus (HBV) if you had a previous infection with this virus.
This can be fatal in some cases. Before receiving daratumumab you should ask your doctor to perform an HBV screening to check if you are positive for HBV. If you previously had an HBV infection, it is recommended you take preventive medicines to protect against the development of an infection.
Questions or concerns
If you have any concerns about your treatment or symptoms, you should speak to your doctor or healthcare team immediately.
What is daratumumab?
Daratumumab is a monoclonal antibody approved in Europe since 2016 for use in myeloma patients. It is used:
- on its own when the disease has progressed despite previous treatment with cancer medicine (including proteasome inhibitors) and immunomodulatory drugs (that act on the immune system), or when the disease has not improved with these medicines
- in combination with lenalidomide and dexamethasone (dara-Rd) or with bortezomib (Velcade), melphalan and prednisone (dara-VMp) in patients with newly diagnosed multiple myeloma who are not eligible for autologous stem cell transplantation (transplant of the patient’s own blood-producing cells)
- in combination with bortezomib (Velcade), thalidomide and dexamethasone (dara-VTd) for the treatment of adult patients with newly diagnosed multiple myeloma who are eligible for autologous stem cell transplant
- in combination with dexamethasone plus either lenalidomide (Revlimid; dara-Rd) or bortezomib (Velcade; dara-Vd) in patients who have previously received at least one other treatment for the disease
As multiple myeloma is considered a ‘rare disease’ because of the small number of patients with this disease, daratumumab was granted ‘orphan drug designation’ by the European Commission in 2013. An orphan drug designation is a status assigned to medicines developed for rare disease conditions that affect fewer than 5 patients per 10,000 inhabitants in the EU.
How does daratumumab work?
Daratumumab is a monoclonal antibody that has been designed to recognise and bind to the CD38 protein, which is found on the surface of myeloma cells. By attaching to CD38, daratumumab kills myeloma cells through a direct anti-tumour activity but it also activates the immune system to find and kill the cancer cells.
What are the benefits of daratumumab?
The safety and efficacy of daratumumab monotherapy (i.e. when given on its own) was demonstrated in two clinical trials. In one study of 106 patients3, 29% of patients had a complete or partial reduction in their myeloma burden, which lasted for an average of 7.4 months. The 12-month overall survival was 64.8% and the median overall survival was 17.5 months. In the second study of 42 patients4, 36% had a complete or partial reduction in their tumour burden. Another significant benefit was the stabilisation of the disease reported in approximately 50% of the patients included in these trials, which is relevant as daratumumab stopped the progression of the disease.
Daratumumab in combination with dexamethasone and either lenalidomide or bortezomib was investigated in two Phase III studies involving patients whose multiple myeloma came back after treatment with other medicines or did not respond to treatment. In the first study5 involving 569 patients, 78% of patients receiving daratumumab and dexamethasone plus lenalidomide for 18 months lived without their disease getting worse compared to 52% of those receiving dexamethasone plus lenalidomide. In the second study6 involving 498 patients, 61% of patients receiving daratumumab and dexamethasone plus bortezomib for 12 months lived without their disease getting worse compared to 27% of those receiving dexamethasone plus bortezomib.
Daratumumab has also been studied in newly diagnosed patients who are eligible for an autologous stem cell transplantation. In the study9, which involved 1,085 patients, daratumumab combined with bortezomib, thalidomide and dexamethasone was compared with a combination of bortezomib, thalidomide and dexamethasone without daratumumab, both given for four treatment cycles before transplantation and two cycles afterwards. After 100 days following transplantation, 29% of patients given the daratumumab combination showed a complete response (no signs of multiple myeloma detectable) compared to 20% of those given bortezomib, thalidomide and dexamethasone alone.
What are the side effects of daratumumab?
Daratumumab can cause infusion-related reactions [IRR] (which may affect around 1 in 2 people), which may cause symptoms such as:
- breathing problems
- cough
- runny or blocked nose
- throat irritation
- nausea (feeling sick)
- vomiting
- chills
However, most IRR occur during the first infusion and are not severe. You should receive medicines to reduce the risk of IRR before and after the infusion and you should be monitored frequently during the entire infusion. Contact a member of the clinical staff if you notice a reaction. Your doctor may need to reduce the infusion rate or stop treatment if you have a severe reaction.
Other common side effects (affecting at least 1 in 5 people) are1:
- fatigue (tiredness)
- fever
- nausea (feeling sick)
- diarrhoea
- muscle spasms
- upper respiratory tract infection (nose and throat infections)
- neutropenia (low white blood cell counts)
- anaemia (low red blood cells)
- thrombocytopenia (low levels of blood platelets)
- peripheral sensory neuropathy (damage to the nerves in the arms and legs)
How and when is daratumumab given?
Daratumumab is given as an infusion (drip) into a vein at a hospital outpatient department or clinic, under the supervision of a doctor who specialises in the treatment of cancer. The starting dose is 16 mg per kg body weight. The subcutaneous formulation of daratumumab is currently approved in Europe for the same indications as the intravenous formulation. Daratumumab subcutaneous is administered as a fixed dose, which significantly reduces treatment time, from hours to approximately three to five minutes, when compared to daratumumab intravenous (IV) formulation.
The dosing schedule for daratumumab subcutaneous infusion is:
- In combination with lenalidomide and monotherapy: daratumumab is given once a week for the first eight weeks, then once every two weeks from week 9 to 24, and then every four weeks onwards until disease progression.
- In combination with bortezomib, melphalan and prednisone : daratumumab is given once a week for the first six weeks, then once every three weeks from week 7 to 54, and then every four weeks onwards until disease progression.
- In combination with bortezomib, thalidomide and dexamethasone:
- Induction therapy: daratumumab is given once a week for the first eight weeks, then every two weeks from week 9 to 16.
- Consolidation therapy: daratumumab is given every two weeks for the first eight weeks
- In combination with bortezomib: daratumumab is given weekly for the first nine weeks, then every three weeks from week 10 to 24, and then every four weeks onwards until disease progression.

References
For a full list of references used to inform this factsheet, please email info@mpeurope.org.